Rights, Stigma and Suicide Prevention
Language, law, and the night that must not be faced alone
32.1 Stigma
Stigma is negative attitude and discrimination. It often stops people seeking help. Education, respectful language, and personal stories reduce it.
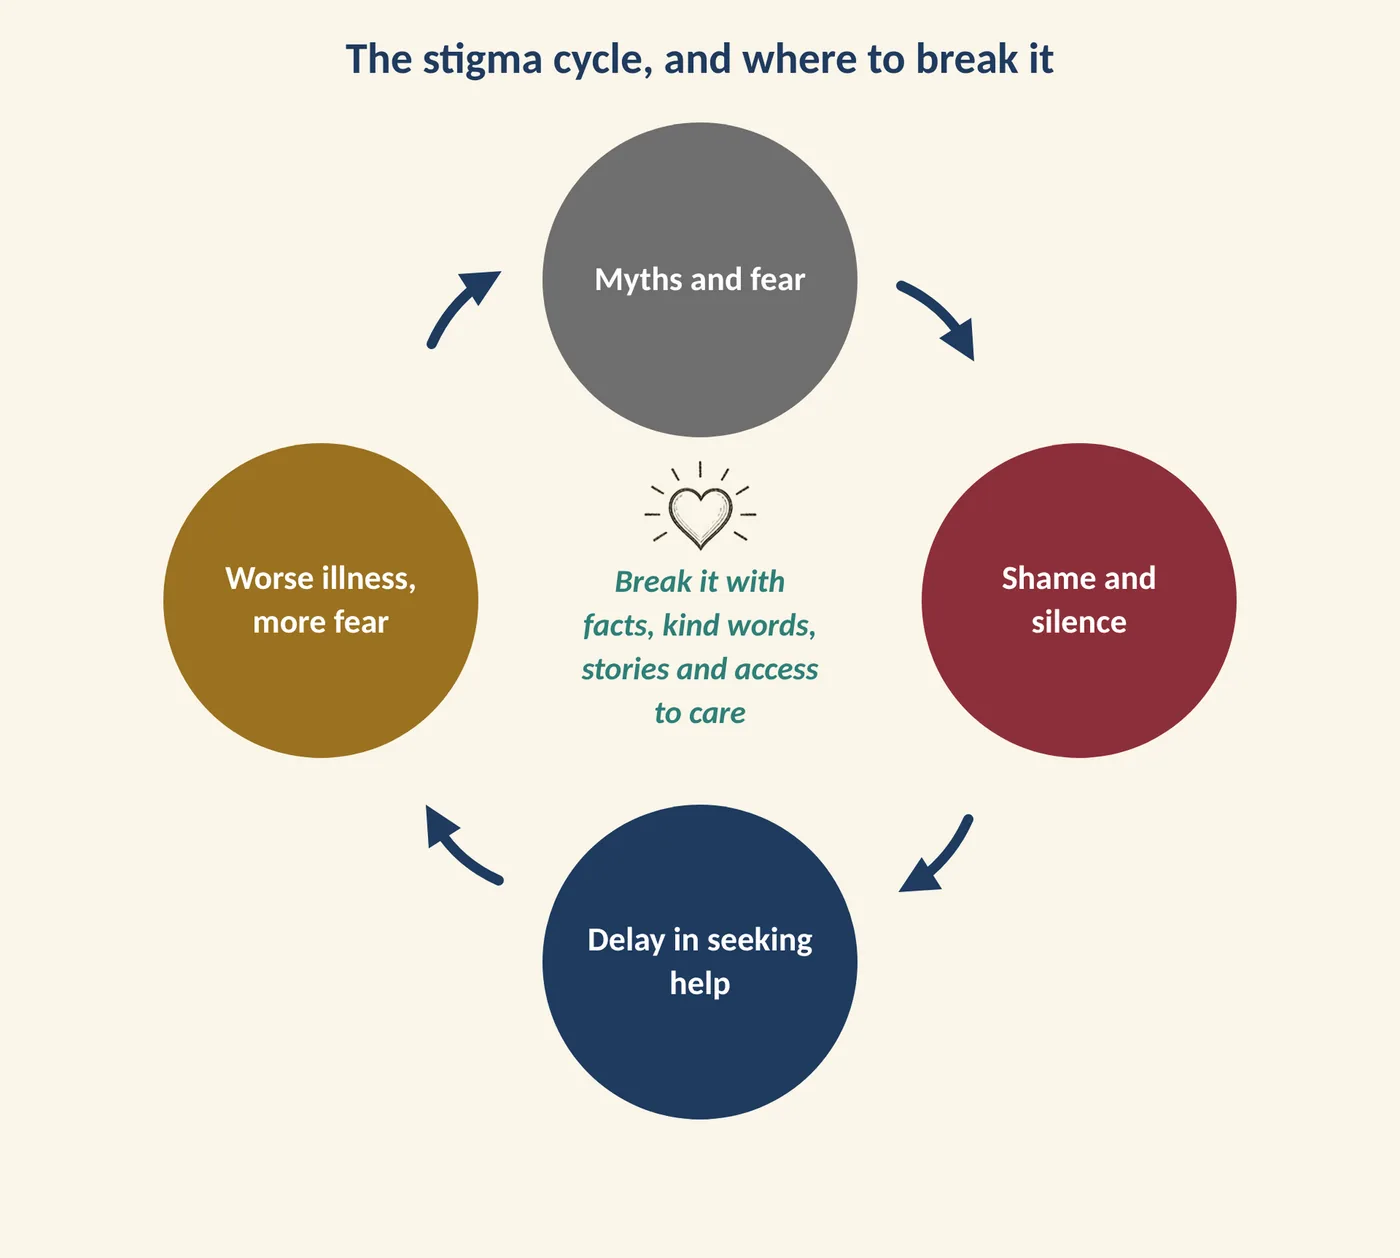
Figure 32.1 The stigma cycle, and where to break it.
People with severe illness are still called mad, dangerous, or hopeless. With diagnosis, treatment, and support, many recover substantial function. Labels should be used carefully. The work is understanding a pattern, not pinning a person to a word.
Adults delay care because of stigma, work, and family duty. Some communities hold stigma harder; care still has to respect faith while staying evidence-based.
32.2 Rights
People with severe mental disorders often face discrimination in education, employment, and housing; social exclusion; human-rights violations — neglect, abuse, inappropriate confinement.
WHO and other bodies emphasise:
-
Community-based care over long-term institutionalisation.
-
Respect for autonomy and informed consent.
-
Protection from abuse and coercion.
-
Integration into society with support.
Families reduce stigma by education, respectful language, and inclusion — not by hiding the person or treating the house as a ward.
32.3 Who is pushed further out
-
Women: violence, discrimination, caregiving load.
-
Men: norms that block help; higher completed suicide in many regions.
-
Gender minorities: discrimination, rejection, minority stress, higher self-harm in some studies — care that is affirming, not a debate.
-
Workplace harassment, and workplaces with no policy against it.
32.4 Suicide prevention
Suicide is a leading cause of death globally, especially among young people. Depression, substance use, trauma, and severe stress are major risks. Warning signs and actions are given here because prevention is also a rights issue: the person is still a citizen tonight.
-
Take talk of death, goodbye, and looking for means seriously.
-
Ask directly. It is a myth that asking plants the idea.
-
Do not leave them alone.
-
Remove access to means if you safely can.
-
Call emergency services. Keep local numbers written down.
Self-harm in adolescents can be a way to cope with pain and is still a reason for care. A plan or attempt is a medical emergency.
32.5 What a family can actually do
-
Use ordinary words: illness, help, clinic — not insult.
-
Share accurate information; stop the joke that makes the room unsafe.
-
Go with the person to the first appointment.
-
If the law is being broken — confinement, beating, locked starvation — that is not culture. That is harm. Seek help outside the house.
Volume 7 in one page
-
25 Addiction.
-
26 Eating disorders.
-
27 ADHD and neurodiversity.
-
28 Digital life.
-
29 Work and study.
-
30 Perinatal.
-
31 Later life and dementia.
-
32 Rights, stigma, suicide prevention.
All of it was already in the text as scattered lines. This volume gives those scattered ideas full chapters of their own.
32.6 Understanding stigma
Stigma is a set of negative attitudes and beliefs about people because of a condition or characteristic. In mental health, it appears in three forms.
| Form | Description | Example |
|---|---|---|
| Public stigma | Society’s prejudice and discrimination | Jokes about “crazy” people; refusing to hire or rent |
| Self-stigma | Internalising negative beliefs | “I’m weak; I should hide this.” |
| Structural stigma | Policies and systems that disadvantage people | Underfunded services; unfair laws |
The harm stigma does
-
People delay or avoid seeking help
-
Shame, secrecy, and loneliness increase
-
Discrimination in work, housing, and relationships
-
Families hide the illness
-
Services receive less funding
-
Recovery takes longer
Where stigma comes from
Fear of the unknown, myths, inaccurate media portrayals (the “dangerous madman” in films, for example), and cultural or religious beliefs that treat mental illness as punishment, weakness, or spiritual failure. In some places, people with mental illness are still chained or hidden. Change is possible: when people learn the facts and meet those who live well with mental illness, attitudes shift.
32.7 How to challenge stigma
As an individual
-
Learn the facts and share them.
-
Use respectful language. Say “a person with depression,” not “a depressive”; say “died by suicide,” not “committed suicide”; avoid “crazy,” “mental,” “psycho” as insults.
-
Speak up when you hear jokes or myths: “That’s not accurate, and it hurts people.”
-
Share your own story, if and when you wish. Personal stories are powerful.
-
Treat people as people, not as diagnoses.
-
Listen to people with lived experience.
-
Support inclusion at work, school, and in the community.
As a parent or teacher
-
Teach children that mental health is as important as physical health.
-
Use books, discussions, and role models.
-
Normalise talking about feelings.
As a leader
-
Set up policies that support mental health.
-
Train managers.
-
Give equal attention to mental and physical health.
-
Fund services.
In the media
Responsible reporting avoids sensationalism, avoids detailed descriptions of suicide methods, shares messages of hope and help, and includes voices of people with lived experience.
32.8 Self-stigma: if you feel ashamed
If you carry shame about your own mental health condition:
-
Remind yourself that it is a health condition, not a character flaw.
-
Talk to someone you trust.
-
Connect with others who have similar experiences through peer support groups.
-
Notice self-critical thoughts and challenge them.
-
Focus on your strengths and goals.
-
Remember that seeking help is a sign of courage.
32.9 Community-based support
Communities can build mental health in many ways:
-
Peer support groups: people with shared experiences help each other.
-
Faith and cultural groups: can offer belonging and meaning.
-
Community health workers: in places with few specialists, trained local workers deliver simple, effective treatments.
-
Online communities.
-
Workplace and school programmes.
-
Green spaces, sports clubs, arts programmes, and volunteering.
Mental health is not only an individual matter. Safe housing, decent work, education, and freedom from violence are mental health issues too.
32.10 Becoming an advocate
If you want to make a difference:
-
Volunteer for a mental health charity (after training).
-
Take a mental-health first-aid course in your area.
-
Organise awareness events in your school, workplace, or community.
-
Support organisations that campaign for better services.
-
Vote and speak for mental health funding.
-
Join conversations online with accuracy and kindness.
TRY THIS: BE THE ONE WHO ASKS
This week, pick one person in your life you haven’t spoken to for a while, or someone who seems a bit quiet. Send a message or make a call. Say: “I was thinking of you. How are you doing, really?” Then listen. A five-minute conversation can be a lifeline.
VIDYA-DANA NOTE
Stigma is a failure to share knowledge: where people know, they stop fearing. Giving a clear fact to someone who is afraid is the quietest and most effective act of care. It is exactly what the tradition calls the highest gift.
अन्नदानं परं दानं विद्यादानमतः परम् ।
अन्नेन क्षणिका तृप्तिर्यावज्जीवं च विद्यया ॥
annadanam param danam vidyadanam atah param |
annena kshanika triptir yavajjivam ca vidyaya ||
Reference — Traditional Sanskrit subhashita (widely quoted; source uncertain)
Key points to remember
-
Stigma delays care; language is part of treatment.
-
Community care and consent are rights, not favours.
-
Asking about suicide does not create suicide.
-
Locking a person up at home is not treatment.
IF TONIGHT IS DANGEROUS
Stay. Ask. Call. This book does not replace a clinician or an emergency department.