Child, Teen and Adult Mental Health
The same mind in different seasons : Age changes the language of distress. Ageing is not a diagnosis.

12.1 Mental health across the lifespan
Mental health needs and challenges change with age. Children, adolescents, adults, and older adults face different developmental tasks, stressors, and vulnerabilities. Understanding these differences helps in early recognition and the right door.
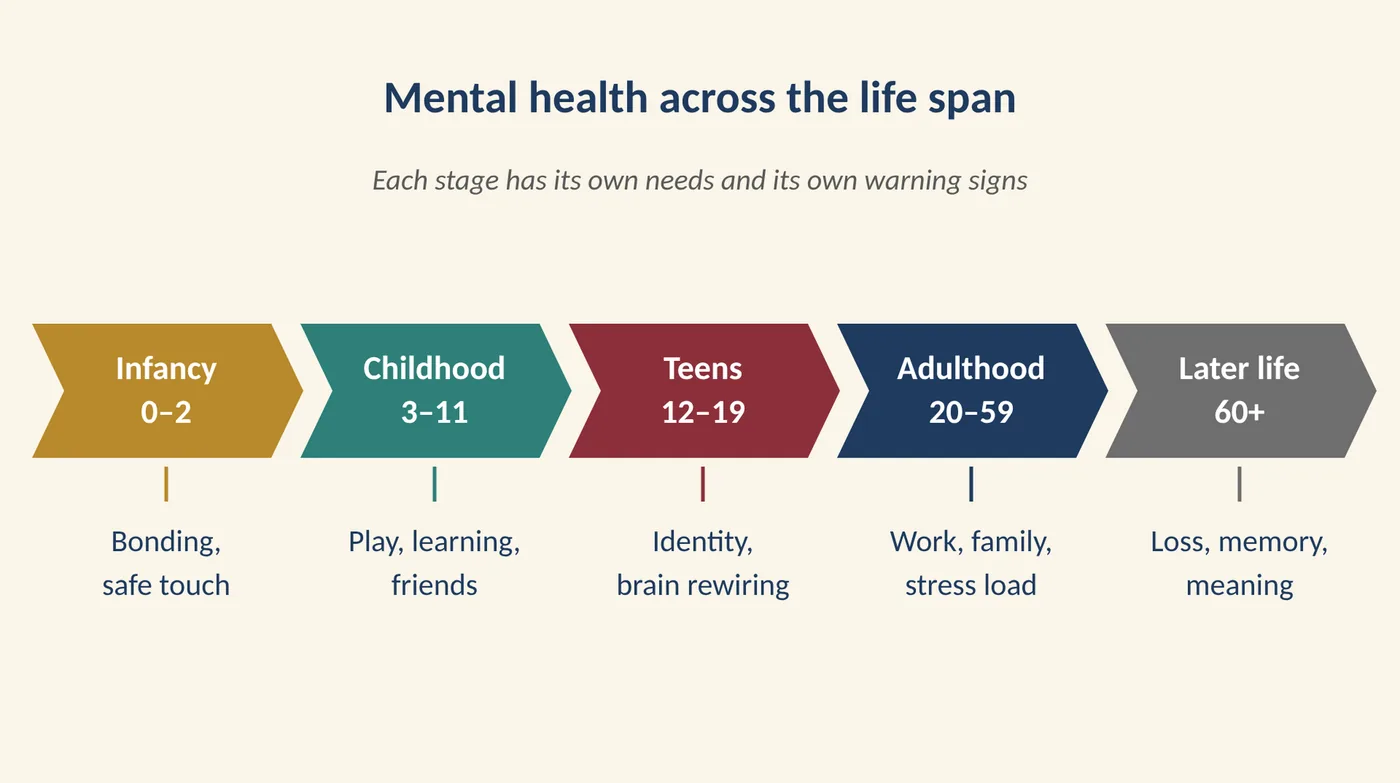
Figure 12.1 Mental health across the life span.
12.2 Child mental health (roughly up to age 12)
Developmental context
Childhood is a period of rapid growth in: brain development and neural connections; language, cognition, and learning; emotional regulation and social skills; attachment and trust in caregivers.
Common mental-health issues
-
Anxiety: separation anxiety, specific phobias, social anxiety, generalised anxiety. May show as clinginess, school refusal, stomach aches, sleep problems.
-
Depression: may appear as irritability, tearfulness, loss of interest, school decline, somatic complaints rather than classic sadness.
-
Attention-Deficit/Hyperactivity Disorder (ADHD): persistent inattention, hyperactivity, and impulsivity that impair functioning at home and school. Not simply naughtiness; involves neurodevelopmental differences.
-
Autism spectrum conditions: differences in social communication and interaction; restricted or repetitive behaviours and interests; sensory sensitivities (over- or under-reactivity to sound, light, touch, taste).
-
Learning disorders: difficulties in reading (dyslexia), writing (dysgraphia), or math (dyscalculia) despite adequate teaching and intelligence.
-
Behavioural disorders: ODD (Oppositional Defiant Disorder) — persistent angry/irritable mood, argumentative behaviour, vindictiveness. Conduct disorder — more severe violation of others' rights (aggression, destruction, deceitfulness, theft).
-
Trauma-related difficulties following abuse, accidents, disasters, or witnessing violence.
Role of family and school
-
Warm, consistent, and responsive caregiving.
-
Clear boundaries with empathy.
-
Regular routines (sleep, meals, study, play).
-
Limited and age-appropriate screen time.
-
Collaboration between parents and teachers.
-
Safe school environment with anti-bullying measures.
-
Access to school counsellors or child mental-health services when needed.
12.3 Adolescent mental health (roughly ages 13–19)
Developmental context
-
Rapid physical changes (puberty, hormones).
-
Brain development, especially emotion and reward systems; prefrontal control still maturing.
-
Identity formation and independence seeking.
-
Increased importance of peer relationships and social acceptance.
-
Exploration of values, beliefs, sexuality, and future plans.
Multiple changes make adolescents vulnerable to mental-health problems, especially under stress.
Risk factors
-
Poverty, displacement, discrimination.
-
Exposure to violence, abuse, or bullying (including online).
-
Academic pressure and exam stress.
-
Family conflict, divorce, or domestic violence.
-
Substance use (tobacco, alcohol, drugs).
-
Chronic physical illness or disability.
-
Lack of supportive adults or peers.
Common issues
-
Depression and low mood: irritability, withdrawal, sleep and appetite changes, academic decline, self-harm, suicidal thoughts.
-
Anxiety: social, generalised, panic, health anxiety, exam anxiety.
-
Behavioural and conduct problems: aggression, rule-breaking, substance use, risky behaviours.
-
Eating disorders: anorexia nervosa (severe restriction, intense fear of weight gain); bulimia nervosa (binge eating then vomiting or excessive exercise); binge-eating disorder.
-
Substance use disorders: tobacco, alcohol, cannabis, prescription misuse, other drugs.
-
Self-harm and suicide risk: non-suicidal self-injury as a way to cope; suicidal thoughts, plans, or attempts are a medical emergency.
-
Technology: cyberbullying; excessive screen time affecting sleep, study, and mood; social comparison and body image concerns.
Supportive approaches
-
Open, non-judgemental communication with trusted adults.
-
Respect for privacy while ensuring safety.
-
Balanced expectations around academics.
-
Healthy routines (sleep, food, exercise, limited screens).
-
Access to school counsellors and youth-friendly mental-health services.
-
Early intervention for substance use, self-harm, or eating disorders.
WHO emphasises that investing in adolescent mental health brings long-term benefits for individuals and societies.
12.4 Adult mental health (roughly ages 20–59)
Common challenges
-
Work-related stress, job insecurity, long hours.
-
Financial pressures and debt.
-
Relationship issues (marital conflict, divorce, single parenting).
-
Parenting stress and work-family balance.
-
Caregiving for children and ageing parents (sandwich generation).
-
Chronic physical illnesses.
-
Migration, displacement, or cultural adjustment.
These can contribute to anxiety, depression, substance use, and relationship difficulties.
Common conditions
Depression and anxiety disorders (most common); bipolar disorder (often first diagnosed in late adolescence or early adulthood); substance use disorders; stress-related conditions and burnout; psychotic disorders (often beginning in late teens to 30s); personality-related difficulties affecting relationships and work.
Many adults delay seeking help due to stigma, work demands, or family responsibilities. Early support can prevent worsening.
Workplace mental health
Stressful work, harassment, discrimination, and lack of support can harm mental health. Positive workplaces promote reasonable workloads and clear roles; respectful communication; work-life balance; employee assistance or counselling; policies against harassment and discrimination.
Taking mental-health breaks, using leave when needed, and seeking professional help are signs of responsibility, not weakness.
12.5 Older adult mental health (roughly age 60 and above)
Common challenges
-
Retirement and loss of work identity.
-
Bereavement.
-
Loneliness and social isolation.
-
Chronic physical illnesses and pain.
-
Reduced mobility and independence.
-
Cognitive decline and dementia risk.
-
Ageism and marginalisation.
Depression in older adults
Often under-recognised and mislabelled as normal ageing. Signs may include persistent sadness, emptiness, or irritability; loss of interest; sleep and appetite changes; fatigue; excessive worry about health; thoughts of death or suicide. It is treatable and should not be ignored. It can co-occur with medical illnesses and dementia.
Anxiety in older adults
Excessive worry about health, finances, family; restlessness, muscle tension, sleep problems; may co-occur with depression or medical conditions. Treatment includes therapy, lifestyle changes, and when needed medicines adjusted for age and other health issues.
Dementia and cognitive disorders
Dementia is a syndrome involving progressive decline in memory, thinking, orientation, comprehension, calculation, learning capacity, language, and judgement, severe enough to affect daily life. Alzheimer's disease is the most common cause. Other causes include vascular dementia, Lewy body dementia, frontotemporal dementia, and mixed types.
Support
-
Regular social contact (family, friends, community groups, faith communities).
-
Physical activity appropriate to ability.
-
Meaningful activities (hobbies, volunteering, mentoring).
-
Management of physical illnesses and pain.
-
Cognitive stimulation (reading, puzzles, conversations, new skills).
-
Caregiver support and respite care.
-
Professional help for depression, anxiety, or behavioural symptoms in dementia.
Respect, inclusion, and dignity are essential. Older adults are not a burden; they are valuable members of families and societies.
12.6 Gender and mental health
Women: higher reported rates of depression and anxiety in many settings; hormonal factors (cycle, pregnancy, postpartum, menopause); higher exposure to gender-based violence, discrimination, and caregiving burden.
Men: may be less likely to seek help due to stigma and norms around masculinity; higher rates of substance use and completed suicide in many regions; may express distress through anger, irritability, or risk behaviours rather than sadness.
Gender minorities (LGBTQ+): higher risk of discrimination, rejection, violence, and minority stress; increased rates of depression, anxiety, self-harm, and suicide in some studies; need for affirming, non-judgemental care.
Gender-sensitive approaches recognise these differences without stereotyping and ensure equitable access to care.
12.7 Culture, faith and mental health across ages
-
Some cultures emphasise physical symptoms (headache, fatigue) rather than emotional language.
-
Faith practices (prayer, meditation, rituals, community support) can be protective and meaningful.
-
Stigma may be stronger in some communities, delaying care.
12.8 When to seek help at any age
-
Emotional or behavioural changes persist for weeks and affect daily life.
-
Significant impairment in work, study, relationships, or self-care.
-
Thoughts of self-harm, suicide, or harming others.
-
Heavy substance use or dependence.
-
Family, teachers, or colleagues express serious concern.
-
Signs of psychosis, mania, severe trauma reactions, or cognitive decline.
12.9 Infancy: before birth to two years
The brain grows faster in the first years of life than at any other time. By age three, a child’s brain has formed many more connections than adults have, and experience then prunes and strengthens them.
What infants need
Above all, babies need safe, responsive caregivers. When a baby cries and an adult comforts them, the child learns the world is safe and people can be trusted. Psychologist John Bowlby and later Mary Ainsworth described this bond as attachment.
| Attachment style | What it looks like in childhood | Possible adult pattern |
|---|---|---|
| Secure | Uses caregiver as a safe base; comforted when upset | Comfortable with closeness and independence |
| Anxious | Clingy, hard to soothe | Worry about being left, need for reassurance |
| Avoidant | Seems self-reliant, avoids closeness | Discomfort with intimacy, values distance |
| Disorganised | Confused, contradictory behaviour, often after fear or trauma | Difficulty trusting, strong swings in relationships |
Attachment patterns are tendencies, not fixed destinies. Warm relationships later in life, including good friendships and therapy, can create more security.
Signs of healthy early development
Babies typically smile in response to faces in the first two months, babble by six to nine months, say first words around one year, and combine words by age two. Children develop at different speeds, but if a child is not making eye contact, not responding to their name, loses skills they once had, or has very delayed speech, speak with a paediatrician early. Early help makes a big difference.
12.10 Early childhood (2 to 6 years)
Play is how young children learn. They pretend, build, explore, and test limits. Their language explodes, and they begin to understand that other people have different thoughts and feelings. Swiss psychologist Jean Piaget described this as the “preoperational” stage, where thinking is imaginative but not yet fully logical.
Common challenges and what they mean
-
Tantrums: normal in toddlers, who feel big emotions but have few words and little self-control. Calm, consistent responses help.
-
Fears: of the dark, animals, or being alone are common and usually fade.
-
Sleep and eating struggles: common, and often manageable with routines.
-
Separation anxiety: natural, peaks around toddler years.
Supportive parenting
Research Favors an authoritative style: warm and loving, but with clear, consistent rules. This differs from authoritarian (strict, cold), permissive (warm, few limits), and neglectful (little warmth or limits). Children do best with both love and structure.
12.11 Life transitions and resilience
Whatever the age, change is hard: moving, new jobs, illness, loss. Psychologists describe resilience, which is the ability to adapt and recover from difficulty. Resilience is not a trait some people are born with and others lack. It can be built.
What builds resilience
-
Supportive relationships: at least one trusted person who believes in you.
-
Realistic optimism: hoping for the best while planning for challenges.
-
Problem-solving skills: breaking big problems into steps.
-
Emotional skills: naming and managing feelings.
-
A sense of purpose: a reason to get up in the morning, whether family, work, faith, or service.
-
Self-care: sleep, movement, food, and rest.
-
Willingness to ask for help.
VIDYA-DANA NOTE
In the Indian tradition the first teacher of a child is the mother, then the father, then the guru. What a child learns at home about feeling, fear and kindness is its first vidya-dana, and it is given free.
12.12 A simple story
For decades, Ramesh’s life was built on two unshakeable pillars: his busy career and his devoted wife. But within a span of just two years, he lost both. He retired from his job, and shortly after, his wife passed away.
Suddenly, the heavy silence of his empty house became unbearable. Ramesh, who used to be the first one out the door for his morning walks, completely stopped leaving the house. He stopped visiting the temple, barely ate, and lost a significant amount of weight. At night, he stared at the ceiling, unable to sleep. When his children came to visit, he would sit quietly in the corner, staring at the floor, occasionally whispering, "What is the point of living anymore?"
At first, his children did not sound the alarm. Like many families, they fell for a very common and dangerous myth. They whispered to each other, "He is just getting old. This is normal at his age. Of course he is sad."
They mistook a medical crisis for the natural process of aging.
The turning point came when his daughter realised that while grief is normal, giving up on survival is not. She gently insisted they visit a doctor. The physician did not dismiss Ramesh's symptoms as "old age." Instead, he gave the heavy sorrow a proper clinical name: Late-Life Depression.
The doctor explained that major life transitions—like retirement and widowhood—can completely shatter a person's sense of identity and daily rhythm. When the brain loses its purpose and its anchor, it can easily fall into clinical depression, regardless of a person's age.
The treatment plan was gentle but highly structured to rebuild his resilience:
The Biological: Ramesh was prescribed a mild antidepressant, carefully adjusted for his age, to help his brain chemistry stabilise and allow him to finally sleep.
The Behavioural: A neighbour was enlisted to knock on Ramesh's door every single morning at 7:00 AM, forcing him to restart his daily walks.
The Social and Spiritual: The family created a strict schedule for his grandchildren to visit, and he was encouraged to slowly return to his temple community.
The Core Lesson: Life Transitions and Resilience
Resilience during a massive life transition does not mean you don't feel the devastating pain of loss. True resilience means actively building a new structure for your life when the old one collapses.
Over several months, the combination of medicine, morning sunlight, and the laughter of his grandchildren brought the colour back to Ramesh's face. Looking back, his son shared a profound reflection that every family should hear: "We almost let him slip away because we thought depression was just a normal part of getting old. Now we know the truth: no matter how old you are, you still have the right to feel joy."
Reflection activity
-
Which life stage do you feel most connected to right now, and what are your main mental-health priorities?
-
Think of an older person you know. Have you noticed low mood, anxiety, or memory problems? What supportive step could your family take?
-
Name one action to reduce stigma in your family or community.